
Voice
How to calculate the ROI of AI voice agents in healthcare
How to model the ROI of an AI voice agent in healthcare, from cost per call to payback, with sourced inputs and a costed five-provider practice.

By Osman Husain

The ROI of voice AI agents in healthcare is calculated by the time and money an agent saves, divided by the cost to build and run it.
It's evaluated in three ways:
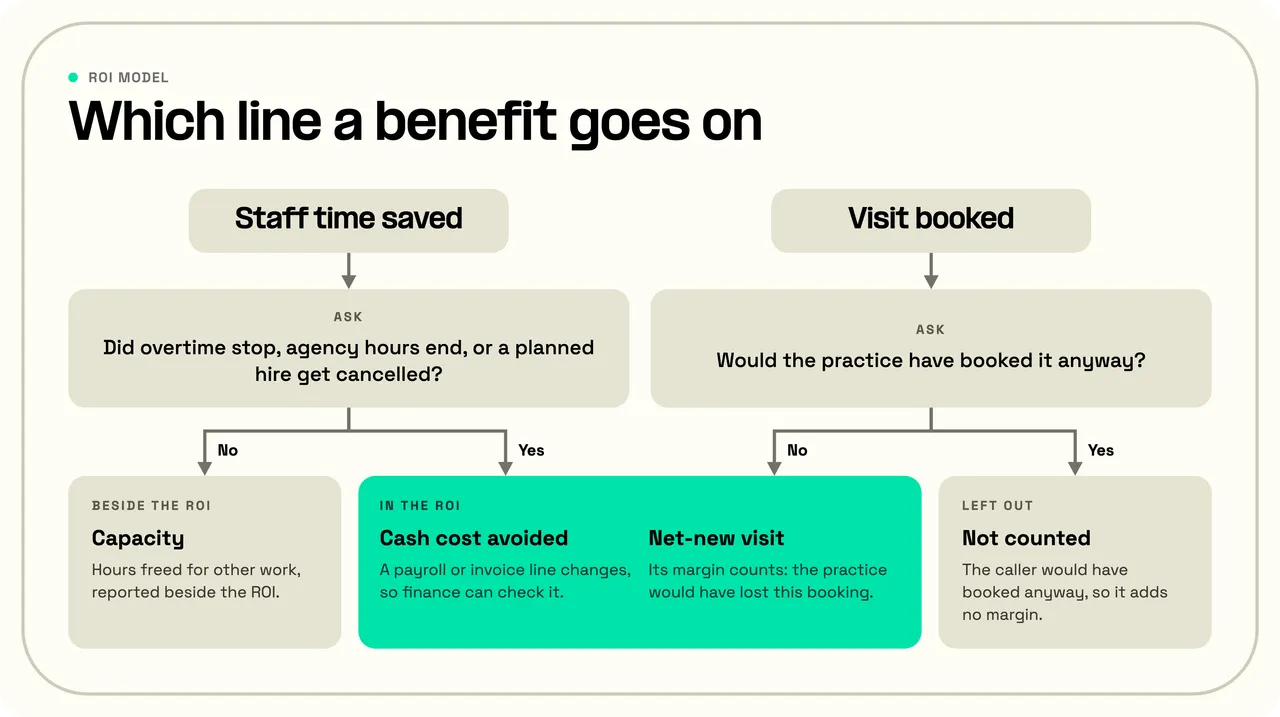
- Staff cost avoided, counted only when overtime, agency hours, or a planned hire go away
- Net-new visits, bookings the practice would otherwise have lost
- Staff hours released, reported as capacity, not cash
Resolution rate (calls finished without staff involvement), net-new visits, and margin per visit are key ROI metrics for healthcare voice AI.
Measuring healthcare voice AI ROI
The metric measures the net benefit an agent produces for each dollar of build and running cost, with a resolved call as the unit of work. The model runs on three formulas:
- Monthly net benefit = cash cost avoided + margin on net-new visits − (agent usage + monitoring and maintenance)
- 12-month ROI = (12 × monthly net benefit − one-time build cost) ÷ (12 × monthly running cost + one-time build cost)
- Payback period in months = one-time build cost ÷ monthly net benefit
A resolved call is one where the caller's task finished with no staff involvement. A call the agent hands to staff is not considered resolved, regardless of how much (or little) of it the agent handled.
The cost of a human attending healthcare calls
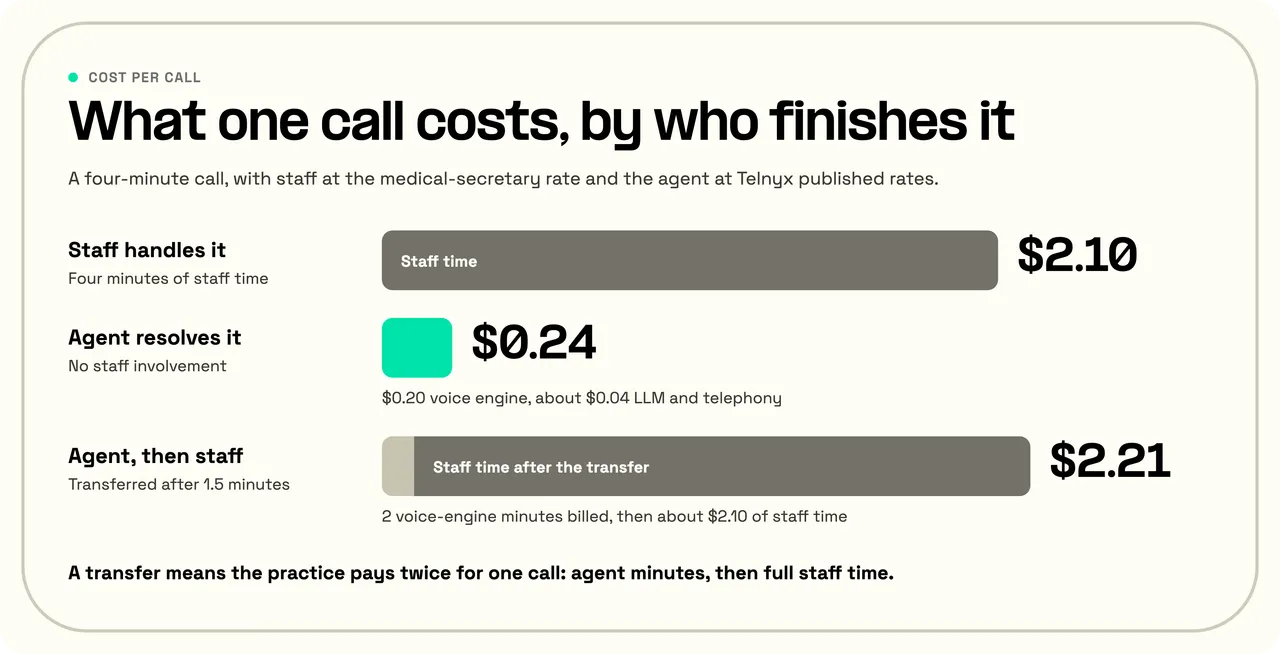
A four-minute call handled by a medical secretary costs a practice about $2.10 in wages and benefits, before supervision, space, or idle time between calls.
The Bureau of Labor Statistics puts the median hourly wage at $22.08 for medical secretaries, $18.27 for receptionists, and $21.53 for customer service representatives.
Benefits make up 30.0% of total compensation in private industry, according to the June 2026 employer compensation costs release, so wages are the other 70%.
Loaded staff cost per call by front-desk role
| Role | Median hourly wage (BLS, May 2025) | Loaded hourly cost | Cost per minute | 4-minute call | 6-minute call |
|---|---|---|---|---|---|
| Medical secretaries and administrative assistants | $22.08 | $31.54 | $0.526 | $2.10 | $3.15 |
| Receptionists and information clerks | $18.27 | $26.10 | $0.435 | $1.74 | $2.61 |
| Customer service representatives | $21.53 | $30.76 | $0.513 | $2.05 | $3.08 |
These cost-per-call figures are the base numbers. Staff are not on the phone for every paid minute, so the full cost is the per-minute figure divided by occupancy, the share of paid hours the phone system shows as talk time. At an illustrative 60% occupancy, the medical-secretary minute costs about $0.88 and the four-minute call about $3.50.

The cost of an AI-handled call
An AI-handled call carries three kinds of cost: usage billed per minute or per token, fixed work that does not scale with volume, and the transfer path to staff.
The rates below are Telnyx's published pricing.
AI-handled call cost lines at Telnyx published rates
| Cost line | How it is billed | Telnyx published rate (September 2026) | What moves it |
|---|---|---|---|
| Voice engine: orchestration (the software that runs the conversation), speech-to-text, text-to-speech | Per minute, each call rounded up to 60-second increments | $0.05 per minute | Call length, share of short calls |
| LLM tokens | Per token | About $0.006 per minute for Kimi on Telnyx GPUs (Telnyx estimate) | Model choice, prompt size, tools, knowledge retrieval |
| Telephony | Per minute, under carrier billing rules | From $0.0032 per minute, US local inbound | Number type, inbound or outbound, country |
| Usage total, typical production agent | Sum of the three lines above | About $0.06 per minute (Telnyx estimate) | All of the above |
| Build and integration | One-time | Quoted per project | Scheduling system and EHR connection, test calls |
| Monitoring and maintenance | Staff hours per month | Internal cost | Transcript review, prompt changes |
| Compliance | Per vendor that touches patient data | No HIPAA add-on fee: HIPAA is included on every Telnyx plan | Number of vendors that handle patient data |
The voice engine rounds each call up to a whole minute, so a 40-second appointment confirmation bills a full minute. Short-call workflows cost more per call than the per-minute rate suggests. Telnyx's cost estimator can give you a precise number.
The LLM is the language model that decides what the agent says, billed by tokens. Telnyx's estimate for Kimi, the model it priced, works out to about $0.006 per call minute. Longer instructions, more knowledge retrieval, and heavier tool use (the agent looking up or writing records mid-call) raise the number.
Telephony is the phone carrier's share. It runs on the Telnyx programmable voice API and bills under carrier rules, so number type, direction, and country set its rate.
The compliance line grows with the vendor count. Each vendor that touches protected health information (PHI) needs a security review, plus a decision on whether it must sign a business associate agreement (BAA) with the practice.
A carrier that only transmits calls can fall under HIPAA's conduit exception, which can spare a vendor that only carries data from signing a BAA. An agent that listens, transcribes, and books appointments does more than carry the call.
Telnyx offers a Business Associate Addendum, its form of the BAA, for its HIPAA-eligible services. Under the Telnyx HIPAA guide, any AI feature that processes PHI must run on a Telnyx-hosted model. The LLM line in a PHI workflow is therefore priced at Telnyx's hosted-model rates, the rates behind the Kimi figure above.
The transfer path is where an agent can cost more than a human. A transferred call costs the practice the agent's minutes up to the handoff plus the full staff handle time, so the practice pays twice for one call.
Voice AI deployments that transfer most of their calls can cost more than answering them with staff alone.
The arithmetic for a four-minute call highlights this. A call the agent resolves on its own costs about $0.24 in usage: $0.20 for the voice engine and about $0.04 for the LLM and telephony. A call the agent transfers after 1.5 minutes bills 2 voice-engine minutes and then about $2.10 of staff time, roughly $2.21 in all. A call that runs a few seconds past four minutes bills five voice-engine minutes.
Telnyx AI Assistants can transfer the call to a staff extension on the practice's existing phone system (its PBX), so staff take transferred calls at their usual desks.
Call transfers with agent context and note-taking are a feature of the top voice AI agents in healthcare, which breaks down developer-friendly platforms versus healthcare-native solutions.
The most profitable healthcare voice AI workflows
Each healthcare call workflow produces a different kind of return, so each one needs its own input and its own baseline.
Return line, input to measure, and evidence by call workflow
| Workflow | Return line | Input to measure | Evidence |
|---|---|---|---|
| Inbound scheduling, rescheduling, cancellations | Capacity, plus revenue where calls went unanswered | Unanswered-call rate by hour, bookings per 100 calls | VA scheduling lines lost about 11% of calls to abandonment (the caller hung up before an answer) in FY2024, against a 5% standard (VA Inspector General) |
| After-hours calls | Revenue, for net-new visits only | After-hours volume, share that books, share that would have called back | The practice's own phone data |
| Payer calls: eligibility and benefits, prior authorization, claim status | Cash where overtime, agency hours, or hires change; capacity otherwise | Payer-call hours per week by transaction type, and which payers still require a call | 2024 CAQH Index: 25 minutes per claim status inquiry by phone; 24 minutes per prior authorization by phone, fax, or email |
| Outbound reminders and recall | Revenue from fewer no-shows, measured against the reminders already in place | No-show and arrival rates by visit type, before and after | Two randomized trials, described below; consent under FCC 24-17 |
| Referral follow-up | Revenue | Referral-to-booked rate | Hello Patient reports 25% to 30% conversion on referral outreach (customer-reported) |
| Refill requests | Capacity | Refill call volume, staff minutes per request | The practice's own phone data |
A scheduling return exists only once the booking lands in the practice's scheduling system. Telnyx Voice AI agents pass each booking to that system through webhook tools.
Reminder calls are considered outbound, and must be done after prior consent. The FCC confirmed in February 2024, in FCC 24-17, that calls using AI-generated voices fall under the Telephone Consumer Protection Act's rules on an "artificial or prerecorded voice."
The benefit side of an AI reminder call should be measured against human-initiated calls. In a randomized trial of 9,835 patients, no-show rates were 23.1% with no reminder, 17.3% with an automated reminder, and 13.6% with a staff call.
Running the reminder calls is the smaller part of the job. Telnyx scheduled events place an outbound call at a set time and retry busy or unanswered numbers. Checking numbers against the FCC's Reassigned Numbers Database before a campaign keeps reminders from reaching someone who never consented.
The payer-call line: phone minutes, cost, and a shrinking volume
An insurance claim status call takes 25 minutes of staff time, the longest of any task measured by the 2024 CAQH Index, an annual benchmark of healthcare administrative costs.
CAQH counts a transaction as manual when it runs by phone, fax, mail, or email. The Index puts a prior authorization at 24 minutes by phone, fax, or email, against 16 through a payer portal. It also puts the provider cost of manual transactions at $13.80 per claim status inquiry, $12.88 per prior authorization, and $8.57 per eligibility check.
Claims calls are long for an agent too. A 25-minute call at about $0.06 a minute costs roughly $1.50 in usage, against about $13.15 of staff time at the medical-secretary rate. CAQH's $13.80 is a blended cost across phone, fax, mail, and email, so the phone-only figure is the better comparison.
That saving holds only if the agent finishes the call, which means getting through the payer's phone tree, waiting on hold, and passing identity checks such as the provider's NPI and tax ID.
Prior authorization calls are the part set to shrink. CMS's Interoperability and Prior Authorization Final Rule (CMS-0057-F) requires the payers it covers, such as Medicare Advantage and Medicaid plans, to offer an electronic prior authorization interface by January 1, 2027. Once a practice's systems can use it, a request that took a phone call can be resolved via software instead.
Payback for a five-provider practice
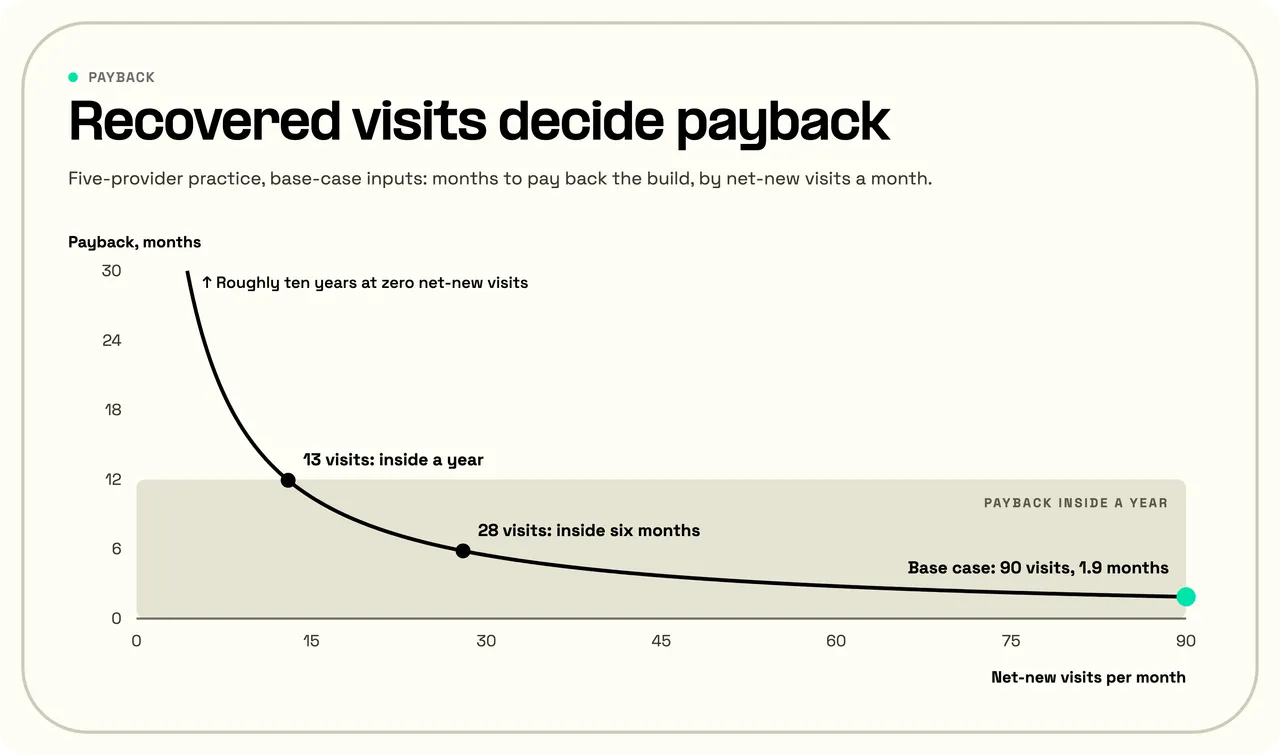
In a hypothetical five-provider practice taking 4,000 calls a month, the voice AI agent pays back its build in about two months. In the downside case, payback takes about five months.
The model in the table below covers inbound patient calls only.
Five-provider practice model, base and downside cases (hypothetical inputs)
| Line | Base case | Downside case |
|---|---|---|
| Inbound calls per month | 4,000 | 4,000 |
| Average staff handle time | 4.0 minutes | 4.0 minutes |
| Calls the agent answers | All 4,000, including the 600 that used to go unanswered | All 4,000 |
| Calls the agent resolves end to end | 45% (1,800) | 30% (1,200) |
| Calls transferred to staff after about 1.5 minutes with the agent | 55% (2,200) | 70% (2,800) |
| Calls unanswered before the agent | 15% (600) | 15% (600) |
| Calls staff handled before the agent | 3,400 | 3,400 |
| Calls staff handle with the agent (the transfers) | 2,200 | 2,800 |
| Unanswered calls that were booking attempts | 50% (300) | 50% (300) |
| Booking attempts that become net-new visits | 30% (90) | 15% (45) |
| Contribution margin per visit | $70 | $70 |
| Cash cost avoided (overtime, answering service) | $1,200 | $600 |
| Monitoring and maintenance | 12 staff hours | 20 staff hours |
| One-time build and integration | $12,000 | $12,000 |
| Agent minutes | 10,500 | 9,000 |
| Voice-engine minutes billed, after rounding | 12,500 | 11,000 |
| Agent usage (voice engine, LLM, telephony) | $726 ($625.0, $67.2, $33.6) | $636 ($550.0, $57.6, $28.8) |
| Monitoring and maintenance at $31.54 per hour | $378 | $631 |
| Monthly running cost | $1,104 | $1,267 |
| Cost per resolved call (running cost ÷ resolved calls) | $0.61 | $1.06 |
| Monthly cash benefit (visits plus cost avoided) | $7,500 ($6,300 + $1,200) | $3,750 ($3,150 + $600) |
| Monthly net benefit | $6,396 | $2,483 |
| Payback period | 1.9 months | 4.8 months |
| 12-month ROI | 256% | 65% |
| Staff capacity released, beyond the overtime already counted as cash (reported, not counted in ROI) | 65 hours ($2,050) | 40 hours ($1,262) |
The model adds about half a minute per call for rounding, applies the LLM at $0.0064 per minute, and telephony at $0.0032 per minute, both to actual agent minutes. Staff time is priced at the medical-secretary rate.
Costs stripped away in the base case have two parts: a $700-a-month after-hours answering service the practice cancels, and 15 overtime hours each month billed 1.5x the normal wage, or about $500. Together they round to $1,200. In the down case, the agent resolves fewer after-hours calls than projected, meaning the practice cannot cancel the service outright.
The model's 15% unanswered-call baseline sits above the 11% abandonment on VA scheduling lines in FY2024 and below the 30% that a single VA call center reached.
What moves payback from two months to five is resolution rate and net-new visits.
Resolution rate also depends on these factors:
- Which call types the agent handles
- Whether its booking write-back works on the first try
- When it hands a call to staff
- Whether it pronounces drug and provider names correctly
The other input, net-new visits, powers most of the upside. The model's 30% is after no-shows are factored in. Thirteen net-new visits a month bring payback inside a year, and 28 bring it inside six months. In the downside case, the first 10 net-new visits each month only cover the running cost.
Margin per visit is the third input that decides AI voice agent ROI.
Talk to Telnyx about pricing a pilot on real call volumes. PatientSync, which handles millions of healthcare calls a year, moved to Telnyx from Amazon Connect, Amazon's contact-center service, and cites per-minute pricing that is simpler to predict.
Measuring ROI during a pilot and after go-live
An ROI model is only as reliable as its baseline data, which means four weeks of phone data captured before the agent answers its first call.
The baseline covers six measures, each with a specific source:
- Calls filtered by intent, from a front-desk tally of why each caller phoned
- Unanswered rate by hour, from the phone system's call-detail or missed-call report
- Average handle time by intent, from the same tally, timed
- Bookings per 100 calls, from the scheduling system's bookings divided by call volume
- Payer-call hours by transaction type, from billing staff timesheets or a short log
- No-show rate by visit type, from the practice management system
During the pilot, each call gets a record: resolved or transferred, the transfer reason, bookings made, and repeat vs net-new appointments.
A workable starting rule counts a booking as net-new when the agent answered a call the old system would have missed, such as after hours or when phone lines were busy. The patient must also have made no other booking request that week for it to qualify as net-new.
Telnyx's structured insights pull the per-call fields from each conversation in a fixed JSON schema, and check against the week's other bookings in the scheduling system.
The Telnyx Mission Control Portal breaks every Voice AI agent call into component costs, with model name and token counts, in the portal and through the API. The per-call cost breakdowns also record the time spent in each component, so billed minutes can be checked against the model's.
The per-call records and cost breakdowns enable monthly reconciliation: the model's cost per resolved call against the measured cost, and the model's cash lines against the P&L. The comparison uses matching weeks, since provider schedules and seasons shift call volume.
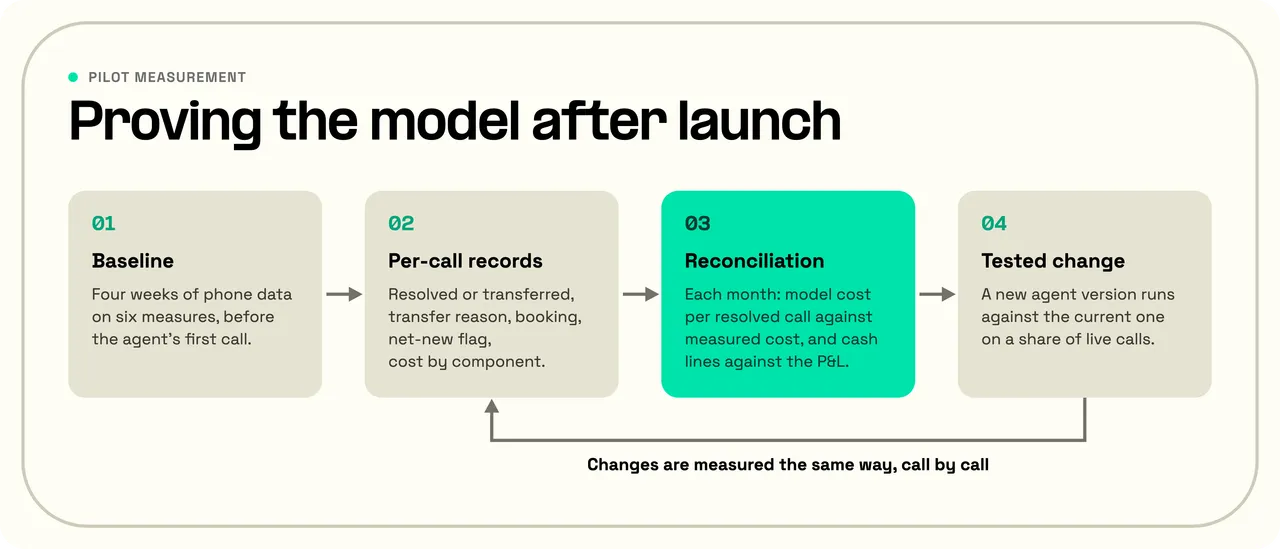
Changes during the pilot get measured the same way, call by call. Telnyx traffic distribution sends a chosen share of live calls to a new agent version, so a change to prompts or tools runs against the current version before it takes all the traffic. Behavior testing, meaning transfers, pronunciation, and failure handling, is a separate job, covered in the pilot test checklist for healthcare voice agents.
Where Telnyx fits in the cost model
The Telnyx Voice AI agent platform runs the voice engine, LLM inference, and carrier telephony on infrastructure Telnyx owns, so one invoice covers the whole call.
The compliance line shrinks the same way: the voice engine, model, and phone layers sit under one BAA, and any third-party integration still needs its own, per the HIPAA guide.
Healthcare companies already run patient calls this way. Hello Patient, whose agents run on Telnyx's Voice AI infrastructure, has powered more than 5 million patient conversations in under two years. Its CEO, Alex Cohen, says customers see double-digit percentage lifts in appointments scheduled.
PatientSync has also built its own products on Telnyx, a a voice AI agent platform with telephony built in, not a pure healthcare app. Healthcare-native products ship scheduling and intake workflows preconfigured, offering a slightly different model to Telnyx for healthcare.
Learn how Telnyx boosts healthcare ROI
Model cost per call with your existing workflows with an expert consultant on the other line.
Contact usFrequently asked questions
What ROI do healthcare organizations typically see from AI voice agents?
Healthcare voice AI ROI figures come mostly from vendors, vary with call mix, and rarely rest on a neutral benchmark. The figure that holds up is an organization's own model of resolution rate, net-new visits, and margin per visit. A hospital or health-system contact center builds the same model; the difference is scale, which makes the transfer path and payer calls larger shares of it.
What ROI can a five-physician practice expect from an AI voice agent?
A five-physician practice's return from an AI voice agent depends far more on resolution rate, net-new visits, and margin per visit than on usage cost. On the hypothetical inputs in the five-provider model in this guide, payback runs about two to five months, and stretches to years when few bookings are net-new.
Can an AI voice agent cut the labor cost of insurance follow-up calls?
An AI voice agent cuts the labor cost of insurance follow-up calls when it can complete the transaction. CAQH reports 25 minutes of provider and staff time per claim status inquiry by phone. The electronic transaction comes first where a payer offers one, and prior-authorization calls are set to fall through 2027. The savings are sizeable only if overtime, agency hours, or a planned hire go away.
How do buyers compare total cost of ownership across healthcare voice AI platforms?
Buyers compare total cost of ownership across healthcare voice AI platforms by evaluating the same cost centers for every vendor: voice engine, LLM, telephony, build, monitoring, compliance, and the transfer path.
Share on Social
Osman is the Global AEO/SEO Lead at Telnyx, helping make voice AI and communications products clearer for builders. With almost a decade of experience in SEO, he previously led growth at Windscribe and Enzuzo, shipping and scaling organic programs that reached millions.


